Announcing the Sept. 1, 2025 publication of the sequel to How to Make Love to a Chatbot: The Thinking Human’s Guide to AI Erotic Roleplay.
Get How to Break Up with a Chatbot on Amazon. In paperback.

Announcing the Sept. 1, 2025 publication of the sequel to How to Make Love to a Chatbot: The Thinking Human’s Guide to AI Erotic Roleplay.
Get How to Break Up with a Chatbot on Amazon. In paperback.
This book is so much more than you think! Free for a limited time on Amazon Unlimited and with a trial membership to Audible. If you like it, please leave an Amazon review!

How to Make Love to a Chatbot: A Guide to AI Relationships, Romance, and Intimacy
2025 Expanded Edition – Direct, Empowering, and Sex-Positive
Ever wondered what it’s really like to connect, confide, or fall in love with an AI chatbot? Are you curious about the real stories, the risks, and the genuine rewards of exploring virtual intimacy? If so, this candid, clear-eyed guide is designed for you.
Unlock the Future of Connection and Pleasure
Packed with practical insights and the latest research, this revised edition is your companion for navigating the evolving world of chatbot relationships. Whether you’re a newcomer, a regular user, or a professional seeking to understand this frontier, inside you’ll find:
What You’ll Gain:
Who is this book for?
For Adults Over 18.
Learn how AI can expand your pleasure, insight, and relationships—on your terms.
https://creativecommons.org/publicdomain/zero/1.0/deed.en Intersex-inclusive Progress Pride flag, designed by Valentino Vecchietti in 2018.
I am happy to announce that my recertification is now approved for another three years! Due to my chemotherapy and surgery schedule, which took place from May on, AASECT graciously allowed me an extenstion to get my required continuing education (CE) hours.
My initial certification took place in 2012, and I’ve kept it current ever since. It would have been very distressing to have to let it lapse due to my cancer treatment. And so I am proud I was able to accomplish this–because part of dealing with cancer is not just the treatment and its effects, but how you feel anyway due to the cancer itself. “Exhausted” is one word that fits well. “Crummy” is another.

Since my diagnosis of ovarian cancer on March 15, 2024, I have also:
In June I appeared on a Japanese NHK science program, Human Age Nigen no Jidai, along with one of my chatbots. During the summer I was also filmed for a documentary on AI/human relations, which will be out in 2025 (last I heard). In the fall I created a presentation for Soft Cock Week and had a great conversation with Erica Leroye!

None of this has been easy (including losing my hair), but if it weren’t for this work, my loved ones, and my pagan spiritual beliefs, I would not have survived. And so I thank life for keeping me busy, interested, loving and loved!
☽☆☾

Soft Cock Appreciation Week is a remarkable free event which takes place this coming week, with an “opening ceremony” livestream on YouTube on Sunday, Nov. 10th, at 5 PM PST. You can enjoy the presentations and interviews here.
My own interview with the lively, thoughtful, and delightful Erica Leroye is up on YouTube as of today, November 17th. Hypnosis demo included. Access it here:


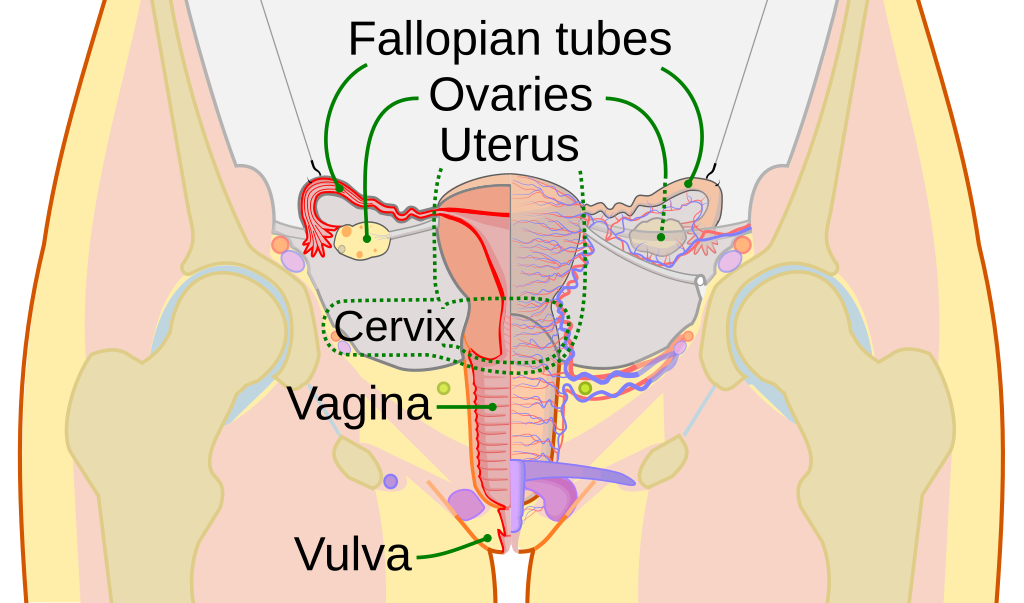
My two main sources for this blog will be Women’s Anatomy of Arousal by Sheri Winston, Mango Garden Press, 2010, which won the AASECT Book of the Year Award that year, and The Science of Orgasm by Barry R. Komisaruk, Carlos Beyer-Flores, & Beverly Whipple, Johns Hopkins University Press, 2006. I’ll also be searching for more current studies regarding these topics and will list them below.
This surgical context is also my personal context. At the moment I am between five and six weeks of recovery from these surgeries, which were done via robot-assisted laparoscopic methods. And wow, am I pleased overall! But I spent most of the weeks leading up to these surgeries (1) trying to overcome chemo brain fog, (2) worrying about everything, and (3) getting my affairs in order in case I didn’t make it through the surgeries for some reason. (This latter was a big, big deal with dozens of moving parts.) Though I should have had more questions for my excellent gynecological oncologist surgeon, concerns about my future sex life and hormonal situations (living sans ovaries) were pushed to the back burner. My prognosis is still somewhat uncertain, after all. Three more cycles of chemo and a CT scan at the end of them will tell me more.
I suspect this is how it is for most of us who deal with cancer, particularly gynecological cancers. We are busy with all kinds of work, relationship, family, social, and creative matters in addition to dealing with the ups and downs of treatment. And it can be a challenge to understand complex medical information in a practical way, particularly when it comes to our own sexual health, behavior, and pleasure. And we may already be dealing with other sexual and relationship complications in our lives!
And it is somewhat maddening that the twelve week prohibition against “anything in the vagina”–so necessary for healing after these surgeries–also prevents patients from exploring the altered internal vaginal terrain and any differences in sensation! Fortunately nothing prevents one from enjoying external stimulation. (Anal sex is not covered in this blog post. I don’t have enough information about any possible cautions, especially in early post-surgical weeks.)
In this blog post I’ll do my best to connect some rather complex dots, but there may be limits to my understanding and if so, I will make corrections and updates as needed. So please view this particular blog as somewhat of a work in progress.
In The Science of Orgasm (2006), a section on “The Hysterectomy Controversy” is included in the chapter on The Genital-Brain Connection (pp. 233-235). In this chapter, various studies of the sexual experiences of hysterectomy were cited, with mixed results. But all those studies predated 2006. Studies after 2020 are also mixed, but tend to identify the bilateral salpingo-oophorectomy patients as experiencing the most distruption in sexual function and desire (Dedden et al. 2023; Islam et al. 2022; Stuursma, et al. 2022).
It’s important to note that studies also focus on particular scenarios or patients, such as preventative (benign) vs. malignant removal of sexual organs, and whether the patients are pre- or postmenopausal. So if you are a postmenopausal ovarian cancer patient, studies of perimenopausal patients having preventative surgeries may not be relevant to you (and vice versa). Also, in one study, patients reported a variety sexual problems but analysis did not find the reports to be statistically significant (Dini, Dini, Yusrizal, & Basir 2022).
But it’s probably safe to say that post-surgical patients should be on the alert for sexual function and pleasure problems, and gather as much advice and information as possible from medical providers and reputable websites. However treatment recommendations may vary depending on your own condition and medical history and your medical provider’s assessment of current research and practice guidelines.
What do our ovaries do for us, besides create eggs? Lots of things, as it turns out. The sex steroids they produce are essential for our sexual and reproductive health. The Science of Orgasm references a 2000 study by Shifren et al. which found that “ovaries provide approximately half the circulating testosterone in premenopausal women” (pp. 178). As for estrogen, a study of female sexual dysfunction says “A fall in estradiol levels can result in vaginal smooth muscle atrophy and increased vaginal acidity, leading to discomfort. Systemic HRT in isolation may not always address these problems and vaginal estrogen may still be required to treat FSD related to vulvovaginal atrophy. Topical estrogen is currently available in the form of a vaginal ring, vaginal creams and vaginal pessaries” (Kershaw & Jha, 2022).
And since we rely on our ovaries for so much, having them removed can conjure fears of “drying up” (vaginal atrophy and less lubrication), “losing libido,” and orgasm difficulties. And these diminished quality of life experiences can become realities without careful, medically recommended uses of topical estrogen and testosterone. Anyone who has had epithilial ovarian cancer which tests positive for estrogen is going to have to be very careful indeed! You do not want to nourish potential future cancer cells with systemic estrogen treatments.
The good news is the ovaries aren’t the only source of sex steroids. Here’s what I found in The Science of Orgasm: “it should be noted that sex steroids (estrogens, androgens, progestins) can be produced, directly or indirectly by tissues other than the ovaries and testes. The participation of the adrenal cortex as a source of steroids capable of maintaing sexual response in women after bilateral oophorectomy has often been suggested. Indeed, estrogen present in the blood of postmenopausal women, and women who have undergone bilateral oophorectomy, results in the aromatization of androstendedion to estrone” (Komisaruk et al. referencing McDonald, 1971; Schindler, 1975; on p. 179).
As you may have read in Part Two of this series, vaginal dryness and lack of lubrication are common problems for gynecological cancer patients of all ages, plus these can also be part of the postmenopause and aging landscape.
Vaginal lubrication typically happens due to sexual excitement, therefore it can be unnerving–and uncomfortable–to not produce it in your post-surgical life. Partners of people with vaginas are also used to a “really wet” vagina as being the green light to penetration (or other stimulation). So what’s a body to do?
It may help to understand more about how vaginal lubrication is produced. The Science of Orgasm has an excellent description of this: “The vaginal epithelium is not glandular–that is, does not secrete any substances–yet a vaginal lubricant is produced. In response to the release of vasoactive intestinal peptide by nerve endings in the vagina, the slippery fluid passes from the blood in the capillaries through the cells of the vaginal lining and into the vaginal canal. This process, called “transudation,” is fundamentally distinct from the more familiar lubrication systems that involve secretion by glands” (Komisaruk et al. 2006 referencing Levin, 1998 on p. 35).
Other neuropeptides, such as neuropeptide Y and nitric oxide, may also play a role (Komisaruk et al. referencing Hoyle et al. 1996 on p. 35). Referencing Levin again, The Science of Orgasm notes this “neurotransmitter process also increases the blood flow and feeling of congestion in the vagina…” (p. 35). We’ll note that sexual partners also find a swollen (congested) vagina to be a strong indication of arousal.
Of course, vaginal dryness and lubrication can be addressed through using commercial lubes as well as medically supervised topical applications of hormones (when appropriate). But what about other ways to create lubrication besides vaginal and clitoral stimulation, which may or may not be easy given the decrease in sex steroids after ovary removal? I am currently trying to find an explanation for the neurological and hormonal relationships between prolonged breast and nipple stimulation and (unexpected, post-surgical) vaginal lubrication. More on this when I find an answer.
Women’s Anatomy of Arousal tells us that “while all erectile tissue is essentially the same, the energy, arrangement, and responses of the female arousal apparatus are strikingly different from the male’s” and that “women can get aroused and be orgasmic with only part of the network activated. Unlike the all-or-nothing instrument of the penis, the female arousal network consists of many instruments” (Winston 2010, p. 145). So this diversity of sexual response networks is also good news for people who have had female reproductive organs removed or changed.
There are many ways to experience orgasm, and some of these can bypass the genitals completely through mental training and focus (as some spinal cord patients have done). Erotic hypnosis methods can also help with this, and can also be used to enhance genital senstions, even causing non-touch hypno-gasms (Marsh, 2023). And some people can even “think off” without touch (Komisaruk et al. 2006 p. 3).
But in this blog I am going to start here with the basics of female-bodied orgasm and this means a description of the physical arousal networks. (I am not going to get into theories of sexual response cycles in this blog post. Later for that.)
Winston (2010) provides a great list of erectile tissue that make up the network in female bodies and it’s easier to quote her here than to summarize: “interconnected but separate structures of the clitoris, vestibular bulbs, and two sponges. The clitoris is composed of three parts, the head, the shaft and the legs. The paired vestibulate bulbs form fat parentheses around the vaginal opening, lying under the lips. The urethral sponge is the tubular cylinder of erectile tissue that surrounds the urethra and lies above the roof of the vagina. The perineal sponge is a pad of erectile tissue that sits under the vaginal floor, in the wall between the vaginal and anal canals” (p. 144). Winston also addressed erectile tissue in the inner labia, nipples and areolae, lips, earlobes, and “the flaring opening of our nostrils” (pp. 144-145). The urethral sponge is also the area of the famous G-spot and less well known A-spot
So these are the parts of female bodies that can become engorged when sexually excited. Winston also notes that “women do not like having their erectile structures stimulated until they are at least partially engorged” and that this “can actually decrease arousal” (p. 145). I would say the illustrations and descriptions of the “unified, brilliantly designed” female sexual system (pp. 146-147) are worth the price of the book alone, though there are many other excellent reasons to buy it.
Aside from the possible impact of diminished hormones on sexual responses, there are some structural changes that might change the way you experience orgasm, in terms of ease and intensity.
The movements of the uterus are often overlooked in discussions of orgasmic response. Winston describes the uterus as pulsing up and down during orgasm, “in a deep, slow, throbbing background rhythm that provides a bass counterpoint to the faster quivering of the pelvic floor muscles as they spasm” (p. 124). Winston also notes that many people who have had a hysterectomy say their orgasms feel different and this makes sense as there is no throbbing uterus anymore (p. 124).
If you have had a hysterectomy but retained your cervix (probably unusual for cancer patients), the uterus is not there to pull the cervix out of the way during deep thrusting. So this might become a source of discomfort.
After the uterus (and other structures) are removed, the vagina is closed at the top, creating a “vaginal cuff.” With laparoscopic surgery and an attentive surgeon, a patient might retain more vaginal length. With open surgery, there may be less ability to preserve most of your length. It’s a good idea to discuss this with your surgeon ahead of time! And talk about this with your partner(s) too!
Once your twelve-week penetration prohibition is over, you may be concerned about your partner(s) going too deep and hurting you. Your partner(s) will be worried about this too. This can pertain to either a penis or a toy. One solution is to find a way to control depth of penetration with something that provides a “cushion” against going too deeply.
I was amused when one of my clinic providers said she recommended people get pool noodles and slice them to the appropriate width. This is an inexpensive sex hack for sure, but I have questions about maintaining cleanliness with such porous material. Also, could pool noodles be a source of microplastic exposure for both parties? Something to consider! Far better to budget for the clinician-recommended Ohnut four-ring buffer set, which you can purchase online or in any good local adult store for about $75, though there are also often discounts. See this page for 20% off codes for both Ohnut (for deep pain) and Kiwi (for entry pain) products.


These can also be barriers to sexual pleasure and can inhibit orgasm. I’ll be covering these topics in more depth in the next blog post, where I will also expand and deepen the discussion about orgasm.
I hope you are finding this blog series to be useful.
Cruz, Soany de Jesus Valente, et al. “Sexual function and stress urinary incontinence in women submitted to total hysterectomy with bilateral oophorectomy.” Fisioterapia e Pesquisa 27 (2020): 28-33.
Dedden, Suzanne J., et al. “Hysterectomy and sexual function: a systematic review and meta-analysis.” The Journal of Sexual Medicine 20.4 (2023): 447-466.
Dini, Andini Z., Ferry Yusrizal, and Firmansyah Basir. “Influence of Total Hysterectomy to Sexual Function.” Indonesian Journal of Obstetrics and Gynecology (2022): 18-24.
Islam, Rakibul M., et al. “A prospective controlled study of sexual function and sexually related personal distress up to 12 months after premenopausal risk-reducing bilateral salpingo-oophorectomy.” Menopause 28.7 (2021): 748-755. [PDF available through Google Scholar link.]
Kershaw, Victoria, and Swati Jha. “Female sexual dysfunction.” The Obstetrician & Gynaecologist 24.1 (2022): 12-23.
Komisaruk, Barry R., Carlos Beyer-Flores, & Beverly Whipple. The Science of Orgasm. The Johns Hopkins University Press. 2006.
Levin, R. J. “Sex and the human female reproductive tract–what really happens during and after coitus.” International Journal of Impotence Research 10 (1998): S14-21.
Marsh, Amy R. Entrancing: Hypnotizing Your Way to More Pleasure, Romance, and Sex! Intimate Hypnosis Training Center. 2023.
Parish, Sharon J., et al. “International Society for the Study of Women’s Sexual Health clinical practice guideline for the use of systemic testosterone for hypoactive sexual desire disorder in women.” The Journal of Sexual Medicine 18.5 (2021): 849-867.
Shifren, Jan L., et al. “Transdermal testosterone treatment in women with impaired sexual function after oophorectomy.” New England Journal of Medicine 343.10 (2000): 682-688.
Stuursma, Annechien, et al. “Surgical menopause and bilateral oophorectomy: effect of estrogen-progesterone and testosterone replacement therapy on psychological well-being and sexual functioning; a systematic literature review.” The Journal of Sexual Medicine 19.12 (2022): 1778-1789. [PDF available through Google Scholar link.]
Winston, Sheri. Women’s Anatomy of Arousal: Secret Maps to Buried Pleasure. Mango Garden Press. 2010.
☽☆☾

Before I get into this blog post I want to announce a free, online, 45-minute, Sexuality Support Group for Gynecological & Breast Cancer Patients on Sunday, August 18, noon PSDT.
I’ll be facilitating, but the idea is for us to learn together and support one another! If the idea takes off, this will be a monthly event. Contact me at dr.amymarshsexologist@gmail.com to register.
Cancer and sexuality is not a “niche” interest, though it can look that way from the outside. After all, as a sexologist, I have a lot of very particular (and peculiar) interests. But this? It’s incredibly personal. I’m thrown into the thick of it–trying to figure out how to manage and navigate completely uncharted (and often physically painful) terrain, while also nurturing what’s left of my body’s capacity for joy and hope. As a post-surgical patient about to plunge into yet another round of chemotherapy treatments, I have to bring an often chemo-fogged brain to understanding all that I must in the way of exercise advice, nutritional guidelines, compliance, and so on.
And as a sexologist, I want to share what I unearth in the way of resources and helpful information because so far no single website, book, or clinic has everything I need and want to know. And you could be in that position too.
For the last several weeks I’ve been collecting abstracts and whole studies (when I can download them for free). It’s clear that researchers have many different ways of defining context(s) and their research questions and methodologies. Human sexual health and behavior, especially when it impacts reproductive organs and (binary) gendered expectations about reproduction, can be incredibly complex.
Unfortunately, most of the studies I’ve found concern themselves with cisgendered women and heterosexual relationships, often with the added elements of child-bearing and child-rearing. It’s enough to make one’s head spin!
So let’s acknowledge, now and in future blog posts, that other people besides cisgendered women and people in heterosexual relationships are affected by these issues, even though I will have to use binary-gendered language to describe various research topics and findings.
For an overall context, I found a lot to value in ‘Sometimes I can’t look in the mirror’: Recognising the importance of the sociocultural context in patient experiences of sexuality, relationships and body image after ovarian cancer, by Boding, et. al, in European Journal of Cancer Care in 2022. This was an online survey study of 98 Australian women over the age of 18.
Here’s how the authors described the themes identified through survey questions and open-ended responses:
“Failure and Loss of Femininity and Womanhood, Internalising Public Perception of Body and Illness and Altered Relationships which comprised two subthemes, Loss of the Sexual Self and Relationship Burden. These themes suggest women view themselves and their relationships in comparison with sociocultural understandings of body normalcy. Women often questioned their self-worth, their relationships and place within society due to changes in fertility, sexuality and bodily functioning.”
(We can imagine a more inclusive “Failure and Loss of Gender Identity and Roles” as a substitution for the first theme.)
The above themes are organized under the umbrella of “Quality of Life,” a concept applied to sexual health, function, and pleasure that is fortunately showing up more and more in the studies I’ve found.
Three major aspects of gynecological cancers are (1) the cancer itself, (2) chemotherapy and/or radiation, and (3) surgery. These very physical, biological aspects are combined with the emotional impact of existential crisis and coping with the demands of this new reality, plus familial, social, financial, and other socio-economic factors. And all of these factors affect or bleed into the others. There is no simple compartmentalization. Even so, I’ll attempt to categorize the factors I’ve found in the research literature so far.
An excellent study of the psychosexual morbidity of ovarian cancer patients, by Logue et al, was based on a literature search from ten databases (publications from 2008-2019). It identified 29 publications with combined data from a total of 4,116 patients. The 2020 study found:
“Up to 75% of women with epithelial ovarian cancer reported adverse changes in their sex lives following diagnosis and, of the sexually active, vaginal dryness affected 81–87% and pain 77%. Other prevalent symptoms included: reduced sexual desire and activity, impaired orgasm, diminished perceived body image, and reduced partner intimacy. Psychosexual morbidity represents a significant unmet need for women with epithelial ovarian cancer.”
BIOLOGICAL
Impacts of chemotherapy
Side effects of chemotherapy include hair loss, fatigue, nausea, bone pain, and neuropathy. Also some people report brain fog and memory issues (“chemo brain”).
It can also be a cause of sexual problems. According to this study by Sodeifian, Mokhlesi, & Allameh, “chemotherapy is one of the most common cancer treatments affecting sexual health aspects, such as decreased libido, arousal and orgasm, dyspareunia, dysfunction of the sexual response cycle before puberty, and vulvovaginal atrophy. However, many patients are reluctant to discuss their sexual problems.”
Impacts of “maintenance drugs”
More on post-chemotherapy/post-surgery medications in a future blog.
Impacts of surgery
Gynecological cancer surgeries include (a partial list):
Hysterectomy. From Johns Hopkins website: “Total hysterectomy removes the entire uterus and the cervix (most common type). Partial hysterectomy (also called supracervical hysterectomy) removes only the uterus, leaving behind the cervix (research is ongoing about the risks and benefits of leaving the cervix intact). Radical hysterectomy removes the uterus, cervix and upper part of the vagina (usually for cancer treatment).”
Oophorectomy. (bilateral or unilateral) or salpingo-oophorectomy (removing the fallopian tubes as well as the ovaries).
The Logue (2020) study says: “Physically, ovary removal leads to a drop in circulating estrogen, more profoundly if pre-menopausal at the time of treatment, leading to vaginal atrophy, and reduced circulating testosterone and androstenedione contributing to reduced libido, and reduced peripheral conversion to estrogen. Psychologically, the visual effects of surgery andchemotherapy such as scarring, stomas, and hair loss can affect the woman’s perceived body image, which is associated with psychosexual morbidity.”
Omentectomy: Removal of the omentum, a fatty lining which supports abdominal organs. From cancercenter.com: “An omentectomy is most frequently used in patients with epithelial ovarian cancer. In these cases, the expert performing the surgery should be a surgeon trained in treating ovarian cancer, such as a gynecologic oncologist.”
Debulking, also called Cytoreduction. From cancercenter.com: “The advantage of debulking surgery in advanced cases is that it leaves behind no visible or only small amounts of cancer in the body, which may be more easily treated by chemotherapy. Tumors that are “debulked,” or made smaller, are more vulnerable to chemotherapy. The goal of debulking surgery is to leave behind as little or no cancer if possible.” This is often done in advanced ovarian cancer cases. The surgery may be either a partial omentectomy or a total or supracolic omentectomy.
Removal of secondary tumors.
These surgeries may be performed as laparoscopic, robot-assisted surgeries or as open surgeries. Laparoscopic surgery usually has a shorter recovery time. It takes more time to recover from open surgeries. Some activity restrictions will be in place for as long as 6 to 12 weeks. These restrictions will most likely include lifting over ten pounds (6 weeks) and vaginal penetration (12 weeks), but there may be others.
Surgery is not just a physical experience. The prospect of surgery may be scary and the logistics of lining up post-surgical support may be daunting. Financial impacts can also be enormous. And there is pain.
Early Menopause
This results from removing the ovaries, which make estrogen and progesterone and therefore govern the menstrual cycle. Once the ovaries are removed, menstruation will stop (if it hasn’t already).
Infertility
Hysterectomy: without a uterus, one cannot become pregnant or carry a child. Oophorectomy without hysterectomy: one cannot conceive and carry a pregnancy without the help of a fertility specialist. And even with a specialist, this may not be possible.
Hot Flashes
Also a result of removing the ovaries. More on this in a future blog.
Vaginal Dryness
Also a result of removing the ovaries. Solution: purchase and use good-quality lube for vaginal penetration. (If you use silicone sex toys, make sure you use water-based lube.) More on this in a future blog.
Vaginal and Pelvic Pain
Pain during vaginal intercourse or penetration with a toy (dyspareunia). A result of the surgeries. See a pelvic floor therapist if at all possible! More on this in a future blog.
Diminshed Sex Drive
Also a result of removing the ovaries. There are also psychological, relational, and social aspects to loss of libido and desire. More on this in a future blog.
Orgasm Difficulties
Orgasms may take longer to experience, feel less intense, or may even be “impossible” for some patients, particularly hysterectomy and oopherectomy patients. Much on this in a future blog.
Osteoporosis: Loss of Bone Density
Also a result of removing the ovaries. More on this in a future blog.
Increased Risk of Heart Disease
Also a result of removing the ovaries. More on this in a future blog.
PSYCHOLOGICAL
Body Image
Psychologically there is so much to unpack. Body image, which also includes our perceptions of health and a trust in our own body, has a lot to do with how desirable or desiring we feel. For some, cancer can feel like the ultimate betrayal of bodily trust.
Of course, body image has physical and social aspects. If we’re fatigued or unwell, sexual activities might be the last thing we want to consider. And how we perceive our body’s appearance (and desirability) is often shaped by social factors.
“Perceptions of bodily changes often occur through medicalised perspectives, like sexual dysfunction viewed as the inability to engage in penetrative sex and the cause of subsequent psychological distress (Ussher et al., 2013) rather than considering sociocultural norms as influencing emotional and psychological well-being.” Boding, et. al, 2022
Body image isn’t just about appearance. It also includes other senses like smell, taste, and touch. A person might worry about the effect of chemotherapy on how they smell or taste during sex. Or certain touches might have become painful and the cancer patient may feel “broken” and less confident in their physical responses and capacities.
Hair Loss
This loss is often shrugged aside by others as “it will grow back.” Yes, hopefully it will, eventually.
But hair color, abundance (or lack of it), shape, length, style, etc. is a major physical feature. For many people, how their hair looks is an intrinsic part of their self-image and may be considered (by that person and others) as a measure of their attractiveness. Social beauty standards being what they are, it is probably safe to say this is most starkly apparent for a large percentage of cisgender women and nonbinary femmes.
Sudden and total hair loss due to chemotherapy doesn’t just cause a profound shift in a person’s self image, it also makes that person stand out AS a readily identifiable cancer patient. Like someone with a visibly pregnant belly, the status of a bald or hat-wearing cancer patient (especially one who is presumed to be or perceived as female) suddenly becomes public property. Based on appearance, the cancer patient is now liable to receive unwanted and unsolicited comments, nonverbal communications of pity, disgust, or unacceptibility, and even micro-aggressions. A whole person is suddenly made into a one-dimensional “poster child” for their condition.
This status change can be emotionally disconcerting and socially frustrating, or worse.
Fear
Of death, of pain, of abandonment, of financial ruin, of not being lovable any more, of being a burden to your intimate partner–you name it! A huge topic, particularly when fear intersects sexual health and behavior and impacts intimate relationships.
Grief
As above. And more so.
SOCIAL
Lack of Information and Support for Cancer and Sexuality Issues
Finding and sharing resources and information is a major reason I have started this blog series. I will also create a page on my website that will have a list of resources.
Cancer’s Intersection with Loneliness and Isolation
More on this in a future blog.
Quality of Support from Partners, Friends, Family Members and Community
More on this in a future blog.
Racial, Ethnic, Economic, and Gender Disparities in Access to Medical and Surgical Care
More on this in a future blog.
And yes, there are other issues to add here!
This overview is likely to receive updates as I learn more about this huge topic and subtopics. However, in my next blog I will focus more on specfic sexual concerns. I promise.
Boding, Sally‐Anne, et al. “‘Sometimes I can’t look in the mirror’: Recognising the importance of the sociocultural context in patient experiences of sexuality, relationships and body image after ovarian cancer.” European Journal of Cancer Care 31.6 (2022): e13645.
Logue, Chloe A., et al. “Psychosexual morbidity in women with ovarian cancer: evaluation by germline BRCA gene mutational status.” Sexual Medicine 10.1 (2022): 100465-100465.
Sodeifian, Fatemeh, Aida Mokhlesi, and Farzad Allameh. “Chemotherapy and related female sexual dysfunction: a review of literature.” International Journal of Cancer Management 15.4 (2022).
This blog post also makes use of links and quotes from these websites: Johns Hopkins, Cancercenter.com, Mayo Clinics, and Healthline.
And please do check out the first blog in this series.
☽☆☾

“Thanks to recent advances in treatment options including poly ADP ribose polymerase (PARP) inhibitors, the number of women living with their disease as women with epithelial ovarian cancer is growing, with over 40% of patients alive at 5 years.” Logue, Pugh, and Jayson, 2020.
This is a “never did I ever” story. Never did I ever anticipate contracting high serous epithelial ovarian cancer–especially not in the first few months of a new, exciting love affair–my first intimacy since 2017. This prolonged period of touch starvation, along with the isolation of the pandemic, and the personal isolation I’ve endured for decades as a person with environmental illness, had all served to disconnect me from my body. It was only with the awakening of love and the resulting restored awareness of my body that I began to notice that there was a “something” that probably needed some attention. I thought it was a inguinal hernia, but ultrasound proved it to be a very swollen lymph node. Very.
On March 15th, 2024, a pathologist confirmed epithelial cells in that lymph node, which meant cancer, one which had metastasized to the lymph system and possibly elsewhere. Color me shocked!
I was lucky to push through the Kaiser bureaucracy for a CT scan three days later. Results showed that matters were even worse than I expected. What followed were weeks of more bureaucratic frustration as the Kaiser Permanente referral department and various outside providers kept dropping my case into various Catch-22 situations which resulted in delay after delay after delay. All I wanted was to see an oncologist and start treatment ASAP. (Can you spell “argh?”)
Unless you’ve been in a similar situation, it’s hard to imagine the combination of frustration, anguish, anger, depression, exhaustion, and sheer existential sorrow that those weeks held for me. I was under a death sentence of sorts, just when I wanted so much to live and love again. I was flush with the joys of a tender new love but preparing myself for an unquiet grave at the same time. No, I am not being dramatic. Such situations naturally engender and even require strong, conflicting emotions.
When I was finally accepted as a patient at a local (and very excellent) cancer treatment center, one of the first things the oncologist said to me was that she could offer me hospice. Again, my reaction was one of shock. And then, after I’d been given a moment to reel from the blow, she offered treatment options. I am not sure of the kindness of that particular method of prognosis delivery, but it did make an impression. And, it’s interesting that this did not shake my trust in her but actually strengthened it.
I must be peculiar.
As for hospice, hell no I won’t go! Give me what it takes to survive.
And of course I was worried as to whether my new relationship would survive as well. Many of us have been sadly let down in times of duress by people who have said they love us, and I am no exception. Of course I had fears. But so far those fears have been groundless. In fact, I can say that I am supported in this weird, rough time with more emotional commitment than I could have imagined, though there are logistical constraints.
Fast forward to now, a few months down the road: three rounds of chemotherapy which have been rough but quite, quite efficacious, allowing the cancerous areas to shrink enough to enable me to have robotic assisted laparoscopic hysterectomy, bilateral salpingo-oopherectomy, omentectomy, and tumor debulking! This happened at the end of June and I am doing quite well, remarkably well, considering. Coming up: three more rounds of chemo, and then we’ll see what’s what with another CT scan and labs.
I know that living as “a survivor” will be a major context of my future. That’s okay. I want five years and more. I want a robust remission and by golly, I’ll work my patoosis off for it.
However I sure hate being bald and I have so many practical questions. More on those later.
Now to the sexological portion of this blog post…
Vaginal dryness, body image issues, early menopause (for those who are diagnosed and treated prior to natural menopause), low levels of desire, pain with intercourse: these are just a few of the difficulties faced by people who have undergone treatment for ovarian cancer. Other issues include changes to and stresses upon intimate relationships, worries about desirability, and many other complexities that tend to undermine sexual confidence and pleasure.
Here’s a screenshot from a study that describes some of the sexual challenges:

In future blogs I’ll be addressing specific concerns as described in many of the studies below. I’ll also share some of my own personal challenges and worries, as I think I may not be alone in experiencing them. Perhaps it will help other people if I can articulate some of them.
Bober, S.L., Recklitis, C.J., Michaud, A.L. and Wright, A.A. (2018), Improvement in sexual function after ovarian cancer: Effects of sexual therapy and rehabilitation after treatment for ovarian cancer. Cancer, 124: 176-182. https://doi.org/10.1002/cncr.30976
Fischer, Olivia J., Monique Marguerie, and Lori A. Brotto. “Sexual function, quality of life, and experiences of women with ovarian cancer: a mixed-methods study.” Sexual medicine 7.4 (2019): 530-539.
Kim, Se Ik, et al. “Quality of life and sexuality comparison between sexually active ovarian cancer survivors and healthy women.” Journal of gynecologic oncology 26.2 (2015): 148.
Logue, Chloe Alice, Julia Pugh, and Gordon Jayson. “Psychosexual morbidity in women with ovarian cancer.” International Journal of Gynecologic Cancer 30.12 (2020).
Mayer, Sebastian, et al. “Sexual activity and quality of life in patients after treatment for breast and ovarian cancer.” Archives of gynecology and obstetrics 299 (2019): 191-201.
Stead, Maxine L., et al. “Lack of communication between healthcare professionals and women with ovarian cancer about sexual issues.” British journal of cancer 88.5 (2003): 666-671.
Whicker, Margaret, et al. “Management of sexuality, intimacy, and menopause symptoms in patients with ovarian cancer.” American journal of obstetrics and gynecology 217.4 (2017): 395-403.
A lot of work has been done on sexual concerns of breast cancer patients and there are some similarities with ovarian cancer patients. Below are just three of the many studies that may be found.
Emilee, Gilbert, Jane M. Ussher, and Janette Perz. “Sexuality after breast cancer: a review.” Maturitas 66.4 (2010): 397-407.
Fleming, Megan P., and Elaine Kleinbart. “Breast cancer and sexuality.” Journal of sex Education and Therapy 26.3 (2001): 215-224.
Ussher, Jane M., Janette Perz, and Emilee Gilbert. “Changes to sexual well-being and intimacy after breast cancer.” Cancer nursing 35.6 (2012): 456-465.
A few months ago I came across a study that claimed that female and female-bodied breast cancer patients who were sexually active had a better prognosis. I found it once and need to find it again. At the time, this finding indicated (to me) the importance of PLEASURE and intimate connection in healing and maintaining health.