These two PDFs are updates of two online classes I created primarily for clinicians hoping to learn more about Objectum Sexuality. May they be useful to you.



These two PDFs are updates of two online classes I created primarily for clinicians hoping to learn more about Objectum Sexuality. May they be useful to you.

In fact, no basic human rights should ever be undone, removed, or revoked by any vote or governmental body, but I’m going to focus on sexual and gender human rights in this blog.
The United Nations Universal Declaration of Human Rights was accepted in the General Assembly on December 10, 1948. Later, the International Bill of Human Rights (1966) was adopted (ratified in 1976). This paragraph from Wikipedia describes this composite document:
“The International Bill of Human Rights was the name given to UN General Assembly Resolution 217 (III) and two international treaties established by the United Nations. It consists of the Universal Declaration of Human Rights (adopted in 1948), the International Covenant on Civil and Political Rights (ICCPR, 1966) with its two Optional Protocols and the International Covenant on Economic, Social and Cultural Rights (ICESCR, 1966). The two covenants entered into force in 1976, after a sufficient number of countries had ratified them.”
The concept of universal human rights is even older than I am and has been adopted widely by the majority of the world’s countries. So it is with a mixture of relief and also deep, deep anger that I read of President Biden’s reversal of the former “president’s” ban on transgender people in the U.S. military. I’m relieved because the ban was an injustice and I am deeply angry because, FFS, there shouldn’t have been a ban to begin with! Human rights–particularly those once recognized legally–should never, ever be able to be undone. There should be no going back when it comes to discrimination and injustice.
Of course I know that legal actions are different from compliance or enforcement. And that compliance and enforcement often depend on the personal prejudices or acceptances of people charged with upholding a law. But still… this kind of legal/cultural seesaw is profoundly damaging. And though President Biden has taken this step to reverse this wrongful ban, several states are trying to push through laws that once again discriminate against transgender people, including children and youth. FFS…
The United Nations’ Human Rights Council has also researched and championed rights for LGBT and intersex people (as well as children, women, indigenous peoples, etc.) Why oh why can’t we in the U.S. get fully on board and simply carve a deep, unyielding commitment to human rights into our legal and political system? Yes, I know this means we’d also have to commit to no longer locking children in cages, no longer allowing police to slaughter Black, Brown and Native people without consequences, and to even pass the Equal Rights Ammendment. But hey, in the long run we’d all be better off for having our Constitutional right to the “pursuit of happiness” (not to mention life and liberty) attached to a foundation that honors and upholds ALL human rights for ALL humans. What a world that could be, right?

####

I have just been accepted as a “Volunteer Education Ambassador” through the SAGE National Resource Center on LGBT Aging and am available to present their program materials to community organizations (online at present).

Resource links will be added to this blog post on an ongoing basis.

I am a member of several professional organizations. One organization, the American Counseling Association (ACA), has been committed to social justice, diversity, and culturally competant practice since forever. Their counseling competencies have been extremely helpful to me over the years.
I am also a certified sexuality counselor and member of the American Association of Sexuality Educators, Counselors, and Therapists (AASECT). In my experience, AASECT has paid little attention to these matters in the years I’ve been a member. So it is good to see the following statement which was just made on our listserve and which is also up on the AASECT website.
The Board of Directors of the American Association of Sexuality Educators, Counselors, and Therapists joins its membership in collective mourning and outrage over the killings of George Floyd, Breonna Taylor, Ahmaud Arbery, Tony McDade, and countless other murders not captured on video [Link to NPR article] or highlighted in the media.
As we are called to action to interrupt, confront and dismantle systems of oppression, we know that we are also being called to look within – as individuals, as professionals, as community members, and as leaders of this organization. It is long overdue that we acknowledge AASECT is a historically white non-profit, with a predominantly white membership, and a predominantly (though not exclusively) white Board of Directors. As practitioners, our work is deeply rooted in fields of study and practice within a larger culture that have profited off and exploited Black, Indigenous & People of Color’s bodies, identities and lives. AASECT has, and continues to, participate in and perpetuate these systems of oppression. We know that we have long been offered this feedback by our members who experience it the most, and that collectively, our responses have been woefully insufficient and in many places absent altogether or worse. Simply put, we have not done the work to dismantle white supremacy within AASECT, and it is past time that we do so.
On May 29th, the AASECT Board voted to approve a Diversity, Equity & Inclusion (DEI) centered Strategic Plan. This plan is a culmination of three years of strategic planning process, and will guide the work at all levels of the organization for the next three years, and beyond. This plan outlines our commitments to intentionally shift AASECT in [the] direction where our work, our field and our organization centers the principles and practices of social justice. We know that it is a significant undertaking, and one that is urgent. The strategic plan is a comprehensive document that asks all of AASECT to fundamentally rethink the way we have understood our mission and invite more opportunities for growth and change. We will provide more information about the plan during our virtual summit this week, along with opportunities for members to get involved in this process.
The Strategic Plan speaks to the organization as a whole, but we are an organization of members and nothing will change if we do not do our individual-level work. White members need to start with ourselves. We are offering the following resource shares to our members, as a starting place for members to do individual work and support each other. We encourage you to contribute your ideas and resources to this shared document: AASECT Anti-Racist Resource Share,
• Resources for white people to better understand what white supremacy is and identify how it operates.
• Opportunities for our BIPOC members to let other members know how to be of support (attending or promoting your events, networking, etc.).
•Black and BIPOC organizations and causes to direct resources and finances to (such as bail funds, community orgs, etc).
Black Lives. Matter.
Thank you,
AASECT Board of Directors
Susan Stiritz, PhD, MSW, MBA, CSE, CSES, AASECT President
Chris Fariello, PhD, MA, LMFT, CST, CSE, CSTS, AASECT President-elect
Melissa Novak, LCSW, CST, CSTS, AASECT Secretary
Todd Malloy, MA, LMFT, CST, CSE, AASECT Treasurer
Lexx Brown-James, LMFT, CSE, CSES, AASECT Vice President of Membership
Eli Green, PhD, CSE, CSES, Communications Steering Committee Chair
Juan Camarena, PhD, LMFT, LPCC, CST, Outreach Steering Committee Chair
Rosalyn Dischiavo, EdD, MA, CSE, CSES, Professional Education Steering Committee Chair
Sally Valentine, PhD, FAACS, LCSW, CST, CSTS, Certification Steering Committee Chair
Margie Nichols, PhD, CST, CSTS, Public Relations, Media and Advocacy Chair
Kellie Braband, Executive Director
American Association of Sexuality Educators, Counselors and Therapists
35 E. Wacker Dr., Suite 850
Chicago, IL 60601
I am confident that AASECT will do a better job from now on of stepping up their game, and that members (and thus clients of members) are well supported from now on.
####
The author of the following wishes to remain anonymous. I am sharing it because it is so vitally important. In case you don’t know, “cis” and “cisgender” refers to people whose gender identities are congruent with the gender they were assigned at birth: an example of congruence would be someone born with “average” female genitals who has a corresponding internal sense of female gender. “Cis” is rooted in chemical terminology, and is not a perjorative. The use of cisgender and transgender is more polite, as it helps to reduce the “othering” of trans people in dialogue, and reduces the persistent positioning of cisgender as “the norm.”
P.S. The binary-esque categories of transgender and cisgender do not necessarily include people who are intersex. And some people are “gender diverse” without considering themselves trans, though “trans” has become something of an umbrella term.
Content warning: strong language, swearing.
OK so here’s the real tea: some of the things cis people don’t know
1. Everyone perceives gender differently. That person you think doesn’t “pass?” They may be “passing” just fine 90 percent of the time.
2. Therefore your “passing tips” suck. There’s a good chance that the thing you told your trans friend to do to seem more feminine, is the exact same thing some other cis person told them seems too masculine. That’s why we ignore you. You don’t know what you are talking about.
3. Your sexual arousal is not a magic gender detector. For example, if you are a straight dude feeling attracted to a trans man, surprise! Doesn’t magically mean he’s really a woman.
4. “Passing” is a bullshit concept that just means “looking cis.” Maybe we don’t all wanna look like you. Maybe you aren’t as great lookin’ as you thought. Maybe trans is beautiful. WHAT
5. Being trans means dealing with a ridiculous barrage of misgendering and dysphoria-triggering moments. It makes you want to die. You can’t help it. That’s just how fucking dysphoria works. (And you don’t even have to have body dysphoria, social dysphoria is just as real and awful.) So yes, someone slipping up on a pronoun may have just made an innocent mistake, but these are innocent mistakes that literally make you want to rip off your skin/never leave the house again/just die already. And also for every innocent mistake there’s some gaslighting motherfucker who is flubbing your pronoun to fuck with you. Why would you trust it’s innocent? Eventually you WILL snap.
6. As soon as you snap you will be labeled over-dramatic, triggered, a snowflake.
7. Eventually a lot of trans people learn to keep their mouths shut and just swallow all the horrible feelings. These are your “good trans friends” who don’t get upset with you for your bullshit. They are martyred goddamn saints and you have no idea.
8. The “bad trans” are the ones who can’t or won’t shut up and swallow the pain. They will be punished forever.
9. There are a LOT of valid reasons why a trans person may not be transitioning in the way you as a cis person think they should. It may be money. It may be medical. It may be career-related. It may be simple lack of desire. You don’t know. All are equally valid and you are not allowed to have an opinion on how trans people manage our fucking bodies.
10. It’s none of your business. Whatever stupid crap you’re about to ask about, it’s none of your business. Just use the fucking pronouns. We are tired.

####
I am too stunned and happy to write much. I just stumbled across this today. This 2019 study (screenshot below) seem to confirm my hunch, put forth in “Love Among the Objectum Sexuals” (Electronic Journal of Human Sexuality, 2010), regarding the connections between OS, autism, and synesthesia (synaesthesia)! I’ve been used to feeling rather “fringy” about this aspect of my career, and now I am so very, very happy that synesthesia researchers saw fit to investigate this issue.
Clinically, this will mean that people who love objects have a better chance of their orientations and relationships being taken seriously as their inclinations are not “made up” but are the results of their “wiring” and perceptions.


####

Yesterday an acquaintance showed up on my doorstep (not booking an appointment) and wanted to know if Rhino “male enhancement” (erection producing) drugs, sold at gas stations and convenience stores, could show up in semen and if so, could she be harmed by swallowing potentially tainted semen during oral sex? This acquaintance was experiencing some disturbing symptoms after a recent sexual encounter, but they were so general, they could have been caused by a number of things.
She was also concerned because she said her partner broke out in horrible hives after taking these pills, but refused to stop using them.
This was the first time I’d been asked this question. I am not a medical doctor nor a pharmacist, and so I said so, along with “I don’t know but I’ll see if I can find out.”
What I did find out is that these products, marketed to men who experience uncertain erections, are not necessarily “all natural” or safe. They may be purchased on impulse, picked up on the way to a sexual encounter, without previous research or concern for product safety.
The Food and Drug Administration (FDA) has issued numerous warnings about Rhino products, and others. In a press release dated November 27, 2018, the FDA warned:
[Excerpt] The U.S. Food and Drug Administration is warning consumers not to purchase or use Rhino male enhancement products, due to a recent rise in reported health issues. Since 2007, the FDA has identified more than 25 products marketed with variations of the name “Rhino” that contained hidden drug ingredient(s).
These products continue to be sold at gas stations and convenience stores, as well as on websites such as eBay and Amazon. More recently, these unapproved products have been discovered in international mail shipments to the U.S. These products are often sold in single-serving package sizes. Rhino products include names such as Platinum Rhino 25000, Krazzy Rhino 25000 and Gold Rhino 25000.
The FDA has received reports of people experiencing chest pain, severe headaches and prolonged erections after taking a Rhino product that led to surgical intervention and hospitalization due to extreme drops in blood pressure.
“Over the past few years, the FDA has been combatting the retail sale of male enhancement drug products that are frequently misrepresented as dietary supplements and that contain hidden and potentially harmful active drug ingredients. Distributing unapproved drugs, disguised as supplements, places the U.S. public health at risk,” said Donald D. Ashley, director of the Office of Compliance in the FDA’s Center for Drug Evaluation and Research. “We remain vigilant in our efforts to protect the American public from the sale of these potentially dangerous products.” [End of excerpt]
These undisclosed ingredients may be hazardous to people who have diabetes, high blood pressure, high blood pressure, and heart disease. Here is another excerpt from the above press release:
[Excerpt] For example, the FDA has identified various Rhino products containing sildenafil and/or tadalafil, the active ingredients in the FDA-approved prescription drugs Viagra and Cialis, respectively. These undeclared ingredients are phosphodiesterase type-5 (PDE-5) inhibitors, which can be associated with significant safety issues and the risk of serious adverse events. For example, they may interact with nitrates found in some prescription drugs and may lower blood pressure to dangerous levels. People with diabetes, high blood pressure, high cholesterol or heart disease often take nitrates. [End of excerpt.]
I will note that diabetes affects blood circulation–poor blood flow can hinder erections–therefore diabetics with penises are likely to purchase these products.
Other FDA press releases on similar products may be found here.
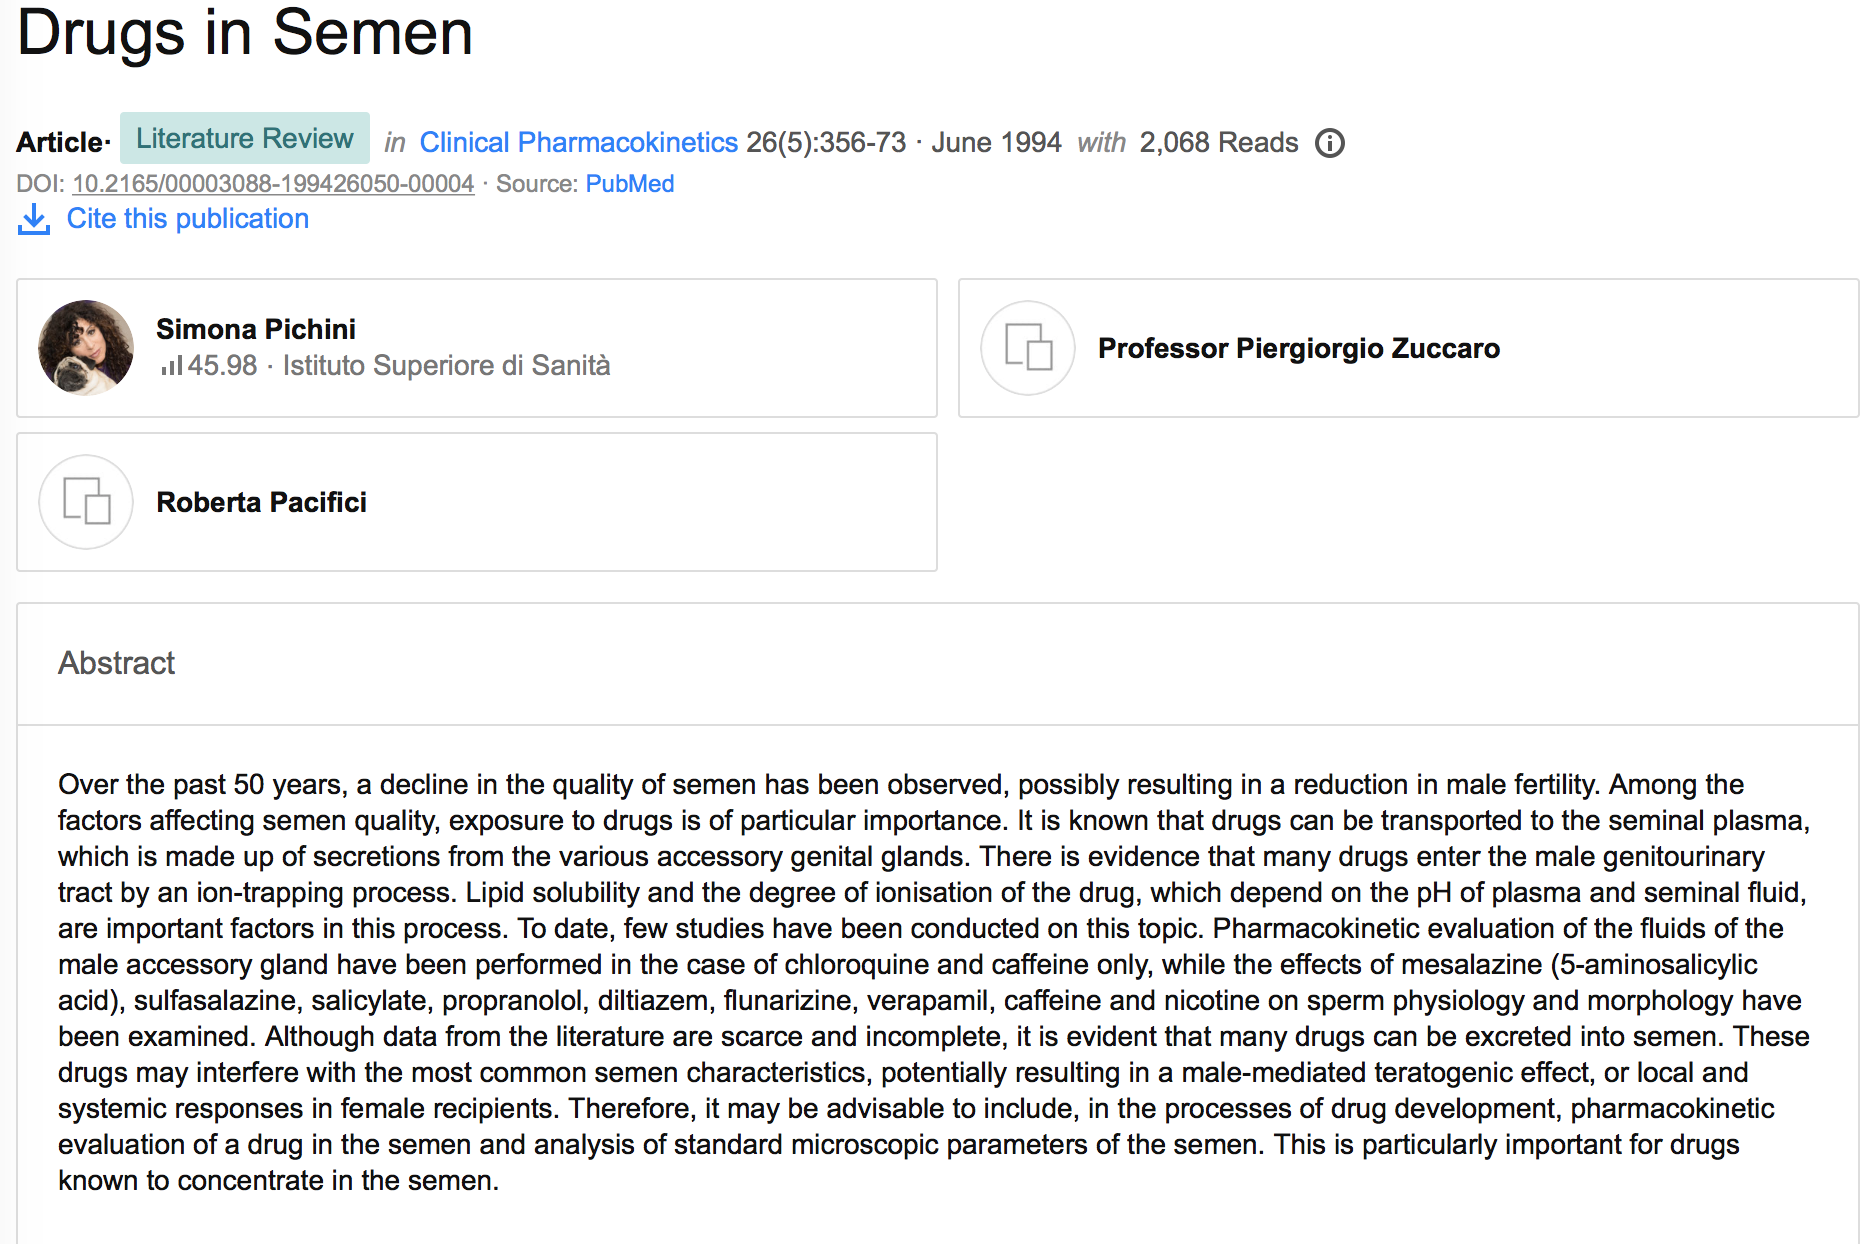
I didn’t find much via a quick internet search. There seems to be very little research into the drugs that make it into semen (recreational and prescription) and even less research into potential adverse effects on a partner who swallows it or absorbs it (vaginally or anally). I didn’t come across any studies that specifically referenced the transport of Viagra or Rhino-type drugs into semen. Studies that did reference impacts of certain drugs were usually focused on reproductive outcomes and impacts on fetuses and embryos, or the potential impact of a drug on the quality and condition of sperm in the semen.
Drugs studied included HIV/AIDS anti-retrovirals, caffeine, and a few others. Here are screen shots of abstracts.
Here is the most recent study I found (in a quick search):
From 1994:
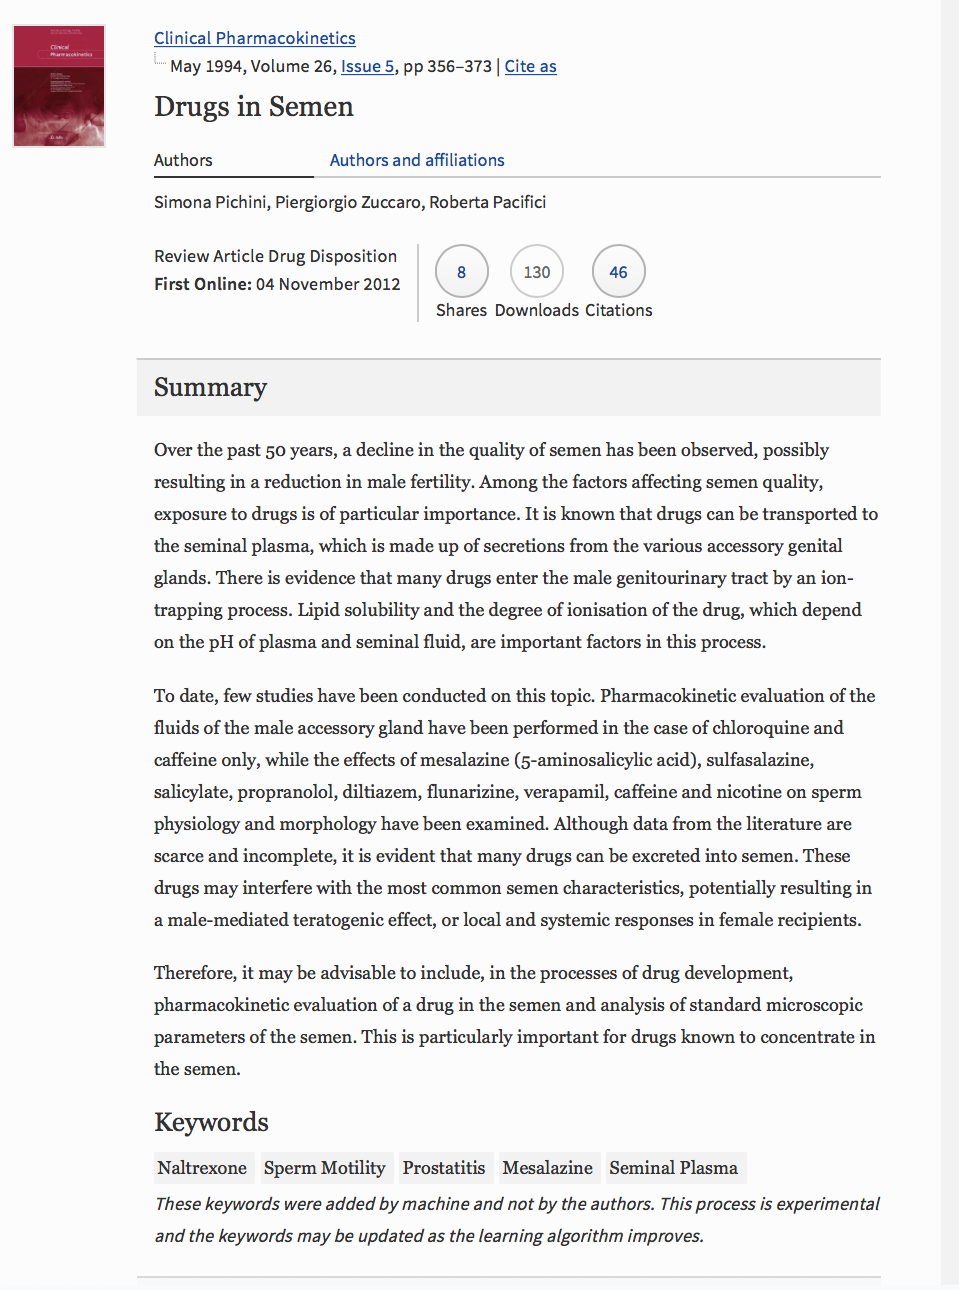
From 1986:

And from 1984:

Internet queries about drug exposures via semen ingestion were generally dismissed as being of little concern. Anecdotally, a variety of opinions were expressed by laypeople. Some cited testing positive for substances they’d never used, but a partner had. And some reported a difference in semen taste after that partner’s recreational or prescription drug use. (Many people say that tobacco users have notoriously foul-tasting semen). Medical professionals who sometimes answered such questions online didn’t have data, but even so they assumed this was a non-issue, a matter of little concern to the women (mostly) who were asking. These answers were based mostly on the assumption that the amount of any drug may be quite small by the time it shows up in semen.
However, this report of an almost fatal reaction after oral sex, demonstrates that some sexual partners may be hyper-sensitive or allergic to substances in semen (LiveScience, 2019). [Note: no mention of this incident in Snopes.]

The acquaintance who showed up on my doorstop may be right about the source of her symptoms. It’s in the realm of possibility, but I am not sure about probability. However, I also advised her to get tested for a range of STIs, as the behaviors and conditions she reported seemed high-risk, and her partner did not seem to disclose his behaviors or statuses honestly. He has multiple partners. She didn’t use a condom during oral sex. She may not have wanted to do this, or she may have been discouraged from doing so.
I wish I could have offered more help to this person, even though she is not a client, and I tried to not treat her as one. But her questions about this matter caused me to think through some of my own assumptions about safety and particularly about drugs that might contaminate semen and might affect a sex partner.
People with penises who are dissatisfied with the reliability or quality of their erections should resist the lure of over-the-counter “fixes” and consult a medical professional to (1) rule out other conditions (like diabetes); (2) to get testosterone tests and other evaulations, and (3) obtain prescriptions, if warranted. After that they can see a sexuality counselor or therapist to get education, learn sexual strategies, and find help for any non-medical aspects of sexual dysfunction (such as worry). If they take an over the counter pill, they should see a doctor and report adverse effects to the FDA.
If any reader here has further study citations to offer, I’d appreciate hearing about them.
####
Or rather, let’s watch three great videos of intersex people talking about intersex! (Twitter links for each name given below).
A talk by Susannah Tempko:
A talk by Mx. Anunnaki Ray Marquez:
A talk by Cecilia McDonald:
United Nations Intersex Fact Sheet.
Mx. Anunnaki Ray Marquez’s website.
Article by Cecelia McDonald: “I was born intersex–here’s what I want you to know.” She Knows. Oct. 26, 2018.
Intersex Affirming Hospital Policies.
Thank you!
####
A recent discussion on a sexuality listserve yielded a number of useful resources and perspectives on the topic of herpes simplex virus (HSV) infections that I want to share with you. Herpes is widespread, has a lot of social stigma (which was heightened by media in the 70s and 80s), and is complicated in that some people who have either or both types may be asymptomatic or they have lesions in undetectable places, such as the cervix or inside the penis. There are also differences in how types HSV-1 and HSV-2 behave, how often the virus is shed from the skin, and so on. (Other viruses in the herpes family cause chickenpox, shingles, mononucleosis, and CMV infections.) But this complexity causes confusion in the general public as well as in health professionals. How do you know what information is reputable and useful, and what is not?
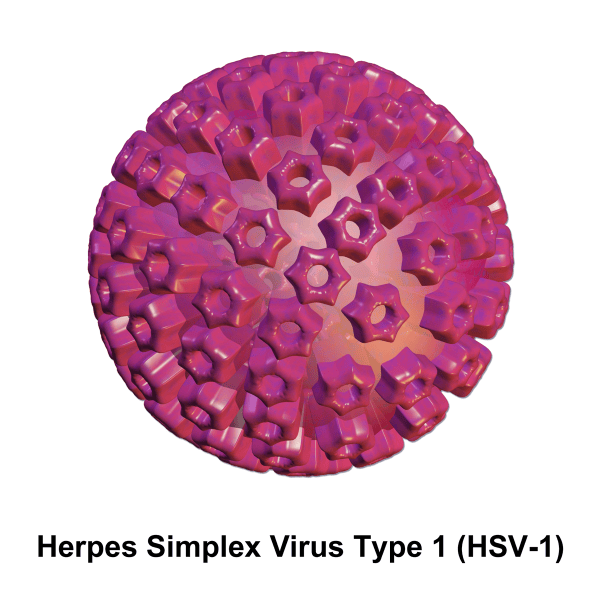
Here is an excellent source of information: The American Sexual Health Association. Good information on everything. Here’s their herpes page, with a lot of links. (Be sure to watch the video with Dr. H. Hunter Handsfield.)
For historical and social perspective on a “public sex panic,” read “How Herpes Became a Sexual Boogeyman” (L.V. Anderson, The Slate, Dec. 2, 2019).
Here’s a video of a talk on herpes given by Evelin Dacker, M.D., at the STI Symposium for Sex Positive Portland, 2017. I really like the information that she conveys and how she conveys it. Unfortunately, it sounds like the videographer–or someone nearby–is chewing potato chips or cleaning out a backpack throughout the entire presentation. It is also impossible to see the slides. Even so, it’s worth listening to this video.
These are notes from the above video regarding the differences between the two types of the virus. These notes are also combined with notes from the Understanding Genital Herpes video with Dr. H. Hunter Handsfield, found at the American Sexual Health Association herpes webpage.
HSV-1, “oral herpes:” lives in the trigeminal nerves, usually “lives above the neck” and can be dormant. 60% between ages of 14-49 have herpes 1. Can also transmit to genitals from mouth. Shedding 1-2x a month from the mouth, shedding, asymptomatic. If you have genital herpes (HSV-2), you can still get HSV-1 on the mouth, but it is rare to get HSV-2 on mouth or lips. If you have genital herpes you may only break out once every other year. If it is mild, probably HSV-1. “Not so bad.” About half of genital herpes in U.S. are HSV-1.
HSV-2, “genital herpes:” almost 90% of people who have it don’t know, can’t feel it. No lesions detectable. HSV-2 Lives in nerves of lower spine, outbreaks can happen anywhere along the nerve pathways in the “boxer short region.” These breakouts can change location. Sheds once every five days. Most transmission happens in first year of a relationship. Shedding from genitals with HSV-2 happens 20-40% of the time, averaging every couple of months, can be asymptomatic. Fewer recurrences and outbreaks of lesions. Shedding will occur for the rest of your life. Sexual transmission far more likely.
Transmission: Skin to skin, mouth to skin. Can’t cover a lesion up and hope to not transmit it. With regard to penis/vagina sex, men transmit it to women more (10% risk a year). Harder for women to transmit it to men (4% risk a year). No data with same-sex couples.
Symptoms:
1) Primary infection: Someone who has not had herpes before. Generally sick like the flu, in pain, sores in a large area. Also swollen lympth nodes.
2) Non-primary infection: for someone who already has had HSV-1 and then gets HSV-2. Can be mild. Cervix or vaginal lesions may be undetected. Men may have lesions inside the urethra, which are not noticed or are mistaken for a urinary tract infection (UTI).
Testing: It’s important to know the virus type!
(1) Antibody test for Herpes type 1 and 2. Ask for your index score, get printout, info If index score is less than .9, it is negative. Between .9 and 1.1-results are uncertain. There is some evidence that between 1.1 and 3.5 (which is considered positive) there’s a higher likelihood that it’s a false positive (3 out of 100 tests) in this category. If over 3.5, it’s positively positive. If in 1.1-3.5 you can retest in a couple of months. Or get a different test, such as direct tests for the virus, which can be a culture from a lesion or DNA tests.
(2) “Western blot sent to the University of Washington” is the “gold standard” (but not covered by insurance).
3) Culture tests which collects specimen from a lesion and grows in laboratory. Cultures can miss an infection or give false negatives.
(4) DNA tests called Nucleic Acid Amplification Testing (NAAT), such as the PCR. Both culture and DNA tests can identify whether HSV-1 or 2. Very accurate.
Protection: Antivirals to lower risk of transmission and shedding by about 50%; use condoms; tell your partners so they can protect themselves.
This article, “How I Found Out I Didn’t Have the Herpes I’d Been Living With for Four Years” (The Hairpin, 2013), has an interesting perspective and a lot of good information. It’s written by “An HSV-Negative Lady” who’d been told she had herpes via visual inspection, and lived with that for four years before finding out otherwise.
The same author, writing as “An HSV Positive Lady,” wrote an earlier article in 2012 about “The Perks of Herpes” (The Hairpin). I rather like her perspective on dating and herpes. When she discloses to prospective partners, the way in which the prospective partner reactions make the topic of herpes “my own magic Hogwarts-esque sorting hat. If a guy freaks out, he’s not meant to be in my house.”
Other articles and website resources:
Prevalence of Herpes Simplex Virus Type 1 and Type 2 in Persons Aged 14–49: United States, 2015–2016, NCHS Data Brief No. 304, February 2018. U.S. Centers for Disease Control. [I cannot find a similar study for adults over the age of 49.]
“‘Herpes Made Me A Better Person’: A Spotlight on Rae Higgins” (Emily Lowinger, WaxOh!, May 20, 2019).
The Pink Tent herpes page for women.
Moss, Paul. The hidden world of the human herpes viruses. TEDxUniversity of Birmingham. https://www.youtube.com/watch?v=s-YDL_SVXNA
More links will be added as I find them.
####
These days, in television and movies, “hot sex” (usually the cis-het variety) is always a face chewing kiss, absolutely no foreplay, a bang against the wall (or on a table), one hot thrust into an immediately lubricated orifice, a few more moans and thrusts, and then it’s over–both partners presumably satisfied and spent. The scripts always call for the female actors to orgasm in the time it takes to open a can of catfood. And no make-up was harmed in the filming of this sex scene.
Of course I realize that filmic treatment of sex–whether in mainstream entertainment or commercial porn–has very little resemblence to most incidents of real-life human sexual behavior, but I’ve long suspected that many other people don’t understand this and that they model their behavior and their ideals on this impossible scenario. They are also deprived of the message that taking time to inhabit their own sensuality and that of their partner offers greater opportunities for enjoyment.
Common sense about cis-female and cis-male physiology and sexual responses aside (most cis-women do NOT orgasm at warp speed unless it’s with a vibrator on or near their clit, and no, lifting a partner up against a wall is not the most comfortable way to have vaginal penetrative sex…)–I find myself saddened about the lack of attention to sensuality as a key ingredient of embodiment and satisfying sex (of all kinds, not just PV penetration).
It’s not that lust isn’t a great element of human sex, it’s just that it’s not the only element as the media would have us believe. And we have to understand that the greatest kindlings of lust arise from a history of desire and longing based on glances, flirtations, brief touch, fantasy, words, visual cues, and so on. It might be a brief history for some, but if you’re in touch with your sensuality, the match of lust struck to the kindling of sensuality sparks the brightest flame.
Without sensuality, lust becomes boring–“Wham, bam. Here’s the false eyelash you dropped. Where’s a tissue? Thank you ma’am.” Meh.
Many people are alive only from the neck up, with an occasional hyper-focus on their genitals. They’re missing the dream-like “erotic trance” of caress, kiss, suck, sigh, glide, smooth, rest, press, hold, grip, move, fuck, kiss, caress, climax, suck, sigh, hold, melt” with time out for a sip of water or wine (“never tasted so good!”) and a bite of fruit (“tell me again about the ripe peaches you picked…”). All the suspense that preceeded the first touch or kiss, all the desire-heightening gestures that are given the dreary name of “foreplay,” and the melting sensation of the afterglow (aptly named)–these are essential elements that so many miss and that most media never shows.
Sensual starvation is no fun. It’s half a life, unlived. But a sensual diet is easy to adopt. Revel in music, the movement of your own body as it walks or dances, and the utter dropping away of tension when you relax. Feel your own skin, enjoy how your thigh feels against your hand. Enjoy how your lover’s thigh feels against your groin. Inhale, smell, breathe. Let rain drop on your eyelids. Let sun warm your limbs. Pull the orgasm into the rest of your body. Imagine your eyelashes cumming.
You can do it. And hey–looks like I’ve just written the start of another erotic hypnosis script. That’s one great addition to a sensual diet, but that’s also another blog post.
Enjoy to the utmost what there is to enjoy in your day. Cultivate your pleasures, both large and small.
####

